The rare complication that matters: filler in a blood vessel
One systematic review counted 190 published cases of blindness after soft-tissue filler injection. A separate review lineage, counting from 1906, reached 511 by March 2023. Both are floors rather than estimates: a case enters the literature only if someone writes it up, and a usable rate for the underlying event exists for one narrow slice of the people who inject.
What actually happens
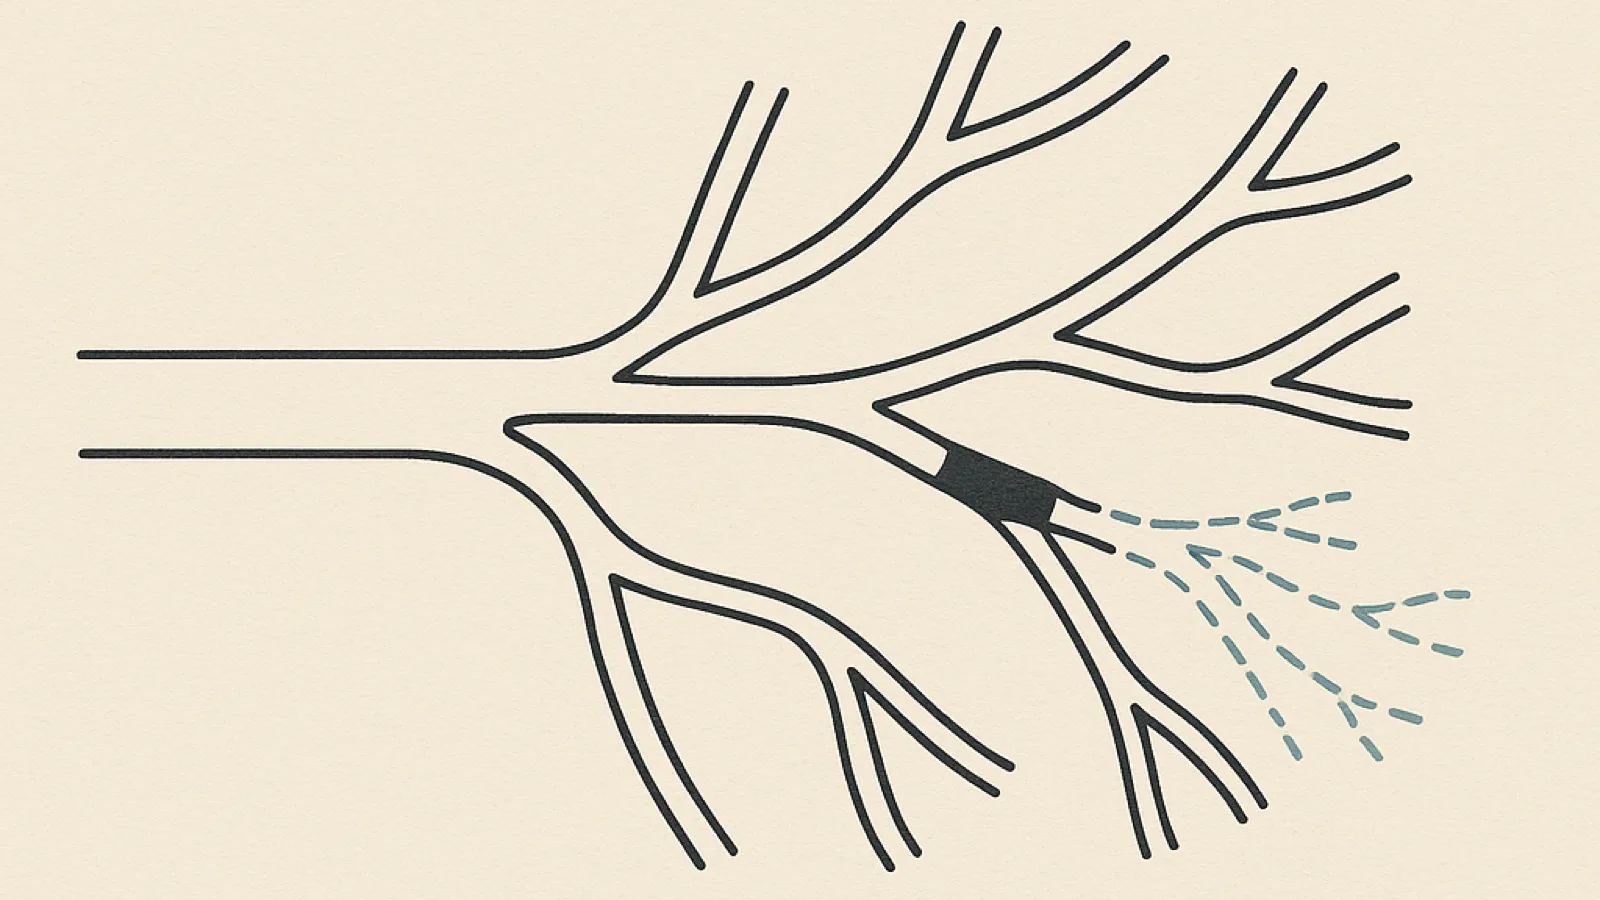
Dermal filler is a gel, placed under pressure through a needle or a blunt-tipped cannula into tissue that also contains arteries. If the tip is inside an artery when the gel is delivered, the gel goes where the blood was going.
FDA sets out the mechanism in the executive summary for its August 2025 advisory panel: the prevailing explanation is “inadvertent penetration of an artery in the face by the needle or cannula and subsequent intra-arterial injection of filler”. Injected under pressure into one of the facial branches of the ophthalmic artery — FDA’s examples are the supraorbital and the dorsal nasal — filler may be carried to the ophthalmic artery itself, “interrupting blood flow to the retina”. Further embolisation, in the same summary, can carry material as far as the internal carotid artery, which is how a facial injection becomes a stroke. The same event in a smaller vessel cuts the supply to an area of skin, and the tissue there dies. One accident; the organ that loses its supply decides how bad it is.
FDA Executive Summary, dermal filler advisory panel, 13 Aug 2025 · rung: label
The material’s chemistry does not cause the occlusion. This is a plumbing event, which is why FDA states that nearly every filler type has been associated with a severe complication leading to visual impairment, blindness or stroke.
What is approved, and what is not
From the label
Fillers. FDA has approved dermal fillers for adults 22 years of age or older. Absorbable fillers are approved for moderate to severe facial wrinkles and folds and for augmentation of the lips, cheeks, chin and back of the hand; non-absorbable fillers only for nasolabial folds and cheek acne scars; separate approvals cover facial fat loss in people with HIV and the correction of contour deficiencies.
What FDA recommends against. On the same page, FDA lists injection of “the glabella (area between eyebrows), nose, periorbital area (around the eyes), forehead, or neck” among uses it recommends against: “These uses for dermal fillers are not approved by the FDA.”
Hyaluronidase. FDA-approved hyaluronidase products carry three indications: as an adjuvant in subcutaneous fluid administration for hydration, to increase the dispersion and absorption of other injected drugs, and in subcutaneous urography. Dissolving filler is not among them.
Treating a complication. “No product has been approved by FDA for use for treatment of filler-related symptoms.”
FDA, Dermal Fillers (Soft Tissue Fillers), content current as of 6 July 2023; HYLENEX recombinant prescribing information via DailyMed, revised November 2024; FDA Executive Summary for the advisory committee panel of 13 August 2025.
Set those lists beside the case literature and something uncomfortable falls out. Among the 365 vision-loss cases in the most recent review of the world literature, the highest-risk sites were the nose (40.6%), the forehead (27.7%) and the glabella (19.0%) — all three on FDA’s list of areas it recommends against injecting. The sites producing most of the published blindness are, in regulatory terms, off-label territory, and a great deal of ordinary practice takes place there.
What FDA actually did. Reports rose sharply in 2014 and 2015; in May 2015 the agency issued a safety communication and worked with manufacturers to revise approved labelling retroactively. The warning it asked them to add states that introduction of product into the vasculature “may lead to embolization, occlusion of the vessels, ischemia, or infarction”, with reported events including “temporary or permanent vision impairment, blindness, cerebral ischemia or cerebral hemorrhage, leading to stroke, skin necrosis”. The precaution states the product “should only be used by health care practitioners who have appropriate training, experience, and who are knowledgeable about the anatomy at and around the site of injection”. That is the regulatory response in full: revised words on a label, and an instruction to be trained and to recognise the event. FDA’s guidance to the person considering the procedure adds one sentence worth reading twice — “Having filler injected should be considered a medical procedure, not a cosmetic treatment.”
What the evidence establishes
The published record on vision loss is a case literature, counted twice, by two groups, using two methods.
One lineage of reviews, by a single group, counts cumulatively from 1906: 98 cases in a 2015 review in Dermatologic Surgery, then 48 more between January 2015 and September 2018 and 365 more between September 2018 and March 2023, both updates in Aesthetic Surgery Journal. The 2024 update states the arithmetic itself — “a cumulative total of 511 cases”, which it calls the largest such review in the literature to date. In the most recent tranche the filler was hyaluronic acid in 79.6% of cases, stroke-like features appeared in 19.2%, and the commonest accompanying signs were skin changes (73.2%), a drooping eyelid (56.2%) and weakness of the eye muscles (44.1%).
Aesthetic Surgery Journal 2024;44(10):1091–1104 · rung: limited
An independent systematic review in Plastic and Reconstructive Surgery — Global Open in 2019 searched a different window and identified 190 cases, 90 of them (47%) involving autologous fat and 53 (28%) hyaluronic acid — fat leading the count even though hyaluronic acid is the material used most widely worldwide. The two totals cannot be reconciled, and that is itself the finding: how many cases exist depends on which databases were searched, over which years, and how duplicate reports of one patient were handled. The 190-case review drew a published comment in the same journal whose title makes the point: A Methodologic Concern Beyond Duplicated Cases. A single tidy figure for how many people filler has blinded is a method quoted as though it were a census.
The outcome data are not in dispute. Of the 318 cases in the 2024 review reporting a visual outcome:
| Outcome | Share of 318 cases |
|---|---|
| No recovery of vision | 68.2% |
| Partial improvement in visual acuity | 25.8% |
| Complete recovery | 6.0% |
The commonest treatments given were hyaluronidase at or near the filler site (70.1%), systemic steroids (57.3%) and intra-arterial thrombolytic therapy (56.0%). None was significantly associated with visual improvement. What did predict improvement was how much sight remained at presentation.
For the underlying event — an occlusion that may or may not reach the eye — the best available rate comes from a retrospective cohort in JAMA Dermatology in 2021, in which 370 board-certified dermatologists reported data covering 1.7 million syringes. The evidence is limited to that one cohort; it found one occlusion per 6,410 one-millilitre syringes injected by needle and one per 40,882 injected by cannula, the risk for any filler type by either route never exceeding one per 5,000 syringes. Eighty-five per cent of the occlusions had no long-term consequence; lips and nasolabial folds were occluded most often, and mean severity was highest at the glabella. One further figure belongs beside the rest: 106 of the 370 participants, 28.6%, reported at least one occlusion. Rare per syringe is not rare per career. The rung marks are explained at how we read the evidence.
FDA’s adverse-event database gives a third view: an all-time search for the dermal filler product codes returned 17,768 serious injury reports, the 2024 tally running to November of that year, with obstruction or occlusion among the commonest serious events named. In FDA’s 2021 panel analysis, 92 reports concerned vision, 77 of them hyaluronic acid, with the nose in 41% of the sites named and 37% of the injuries unresolved at the time of filing.
Where the evidence runs out
Everything above is a numerator. The denominator does not exist.
FDA says so itself, in the 2025 executive summary that presents those same numbers: “the incidence or prevalence of an event cannot be determined from this reporting system alone due to potential under-reporting of events and lack of information about frequency of device use. As a result, the actual number of adverse events is expected to be substantially higher than what is reported through the MDR system.” Manufacturers must report events they learn of; the clinician and the person treated report voluntarily. The true incidence of filler-associated vascular occlusion in the United States has not been established, and no source cited here claims otherwise.
The 2021 cohort is the closest thing to a rate, and its limits are structural rather than fixable. It sampled board-certified dermatologists in professional societies who agreed to fill in forms — not nurse injectors, not dentists, not the wider population injecting filler in the United States. It counted syringes rather than people, and being retrospective and self-reported it counted occlusions that were noticed and remembered. The case reviews have the mirror-image problem: they count publications, not patients, and a complication recognised, treated and never written up appears in none of the 511.
Two further gaps sit underneath reassurances offered routinely. The first is training. It is not clear whether training reduces the risk of this event. FDA’s 2021 panel summary puts it in terms no marketing page would choose: “it is not clear that there is published evidence demonstrating that training does decrease the risk of vascular occlusion-related events… There appears to be a paucity of evidence quantifying the effectiveness of training, or identifying the types of training that may be most appropriate to mitigate risk.” That cohort did find lower odds of occlusion among dermatologists injecting for more than five years — evidence about experience within one profession, not evidence that a particular course works.
The second is the rescue. Hyaluronidase is used because it cleaves the sugar chains hyaluronic acid gel is built from, and FDA calls off-label hyaluronidase injection “a clinically accepted method for removal of a hyaluronic acid filler”. Accepted is not evaluated. The 2025 panel summary states that hyaluronidase and other products “have not been evaluated and approved by FDA for this use related to dermal fillers”, that “recommendations in literature for specific dosage and injection techniques have not been well established”, and that for filler-related vascular occlusion with blindness, “safe and reliable treatment applicable to all fillers has not been identified”. FDA has received 83 adverse-event reports since 2011 about hyaluronidase used this way — commonly swelling, burning, redness, excessive loss of volume, and the product simply not working.
FDA Executive Summary, dermal filler panel, 13 Aug 2025 · rung: not evaluated
The professional literature agrees with the regulator here, which is unusual enough to record. Grading its own recommendations, the American Society for Dermatologic Surgery task force wrote that “the certainty of evidence supporting the effectiveness of injectable hyaluronidase is of lower certainty and is based primarily on observational studies”, then recommended it strongly anyway, on the grounds of what patients value rather than the strength of the data. The review it commissioned found eight case series covering 96 patients treated for injection-related visual compromise, reported “no comparative studies to provide reliable efficacy estimates for the various interventions”, and recorded that 19% had any degree of recovery. UK consensus guidelines published in 2026 are rated by that journal at level of evidence 5, the weakest tier on its own scale. And the premarket trials were never going to settle it: FDA puts their size at 100 to 300 subjects and says that while that is enough to judge whether the treatment works and to characterise common injection-site responses, it “may not adequately characterize less common events such as intravascular occlusion or embolism”.
What it costs, and how it is priced
No published figure describes what a vascular occlusion costs the person it happens to, and this page will not invent one. Three things about the money are on the record. Dissolving hyaluronic acid filler is itself a procedure: FDA’s consumer guidance says removing or reducing filler may take injections, surgery or other interventions, and that those “procedures carry their own risks”. No source cited here treats removal as included in the price quoted for placing the filler. Emergency assessment, ophthalmology and any hospital care sit outside whatever an aesthetic treatment was quoted at. And for filler that is not hyaluronic acid there is no enzyme to buy at any price. FDA’s own suggestion concerns timing rather than cost: it “believes that conversations regarding the benefits and risks of removing dermal fillers may be best prior to injection”.
Risks, in proportion
Common
FDA’s list for approved uses: bruising, redness, swelling, pain, tenderness, itching and rash, mostly appearing shortly after injection and resolving within days to weeks.
Less common
Inflammation near the injection site after an infection, illness, vaccination or dental procedure; raised bumps under the skin that may need medicine or surgical removal; infection; open or draining wounds; allergic reaction; and tissue death.
Rare but serious
Unintended injection into a blood vessel is, in FDA’s words, “the most concerning risk associated with the use of dermal fillers”, and its listed consequences are tissue death, vision abnormalities including blindness, and stroke. Likelihood and permanence belong in one sentence. On the best available estimate the event is rare per syringe, on the order of one in several thousand for a needle injection in that single cohort; when it reaches the eye, 68.2% of published cases reporting an outcome did not recover vision. Something can be both unlikely and unfixable, and that combination is why this article exists.
FDA’s own list of rare reported risks does not stop at the eye. It runs: severe allergic reaction requiring immediate emergency medical assistance; migration of the filler material away from where it was placed; leakage or rupture of the material at the injection site or through the skin; permanent hard nodules; injury to the blood supply from unintended injection into a vessel, resulting in tissue death, vision abnormalities including blindness, or stroke; and death. The last item on that list is printed here because FDA prints it.
Can it be undone
Only partly, and only for one chemistry. Hyaluronidase degrades hyaluronic acid, which is why those gels are called reversible; that use is off-label, the dosing is not standardised, and its effect on blindness is unproven. For calcium hydroxylapatite, poly-L-lactic acid, polymethylmethacrylate and injected silicone, FDA states that “there are no specific reversal agents”, and its consumer guidance warns that removing filler may be “difficult or impossible”. Reversibility is a property of a chemistry, not of the word filler — which is why it is worth knowing what is actually in a filler syringe before the question arises.
When to seek urgent care
If this is happening now
FDA tells people who have had filler injected to seek immediate medical attention if they experience unusual pain, vision changes, a white, grey or blue appearance of the skin near the injection site, or any signs of a stroke — sudden difficulty speaking, numbness or weakness in the face, arms or legs, difficulty walking, visual changes, face drooping, severe headache, dizziness or confusion — during or shortly after the procedure. The signs clinicians are told to treat as an emergency are the same ones, plus blanching of the skin at or around the treated area.
Timing settles nothing. In FDA’s analysis of vision-related reports, symptoms began immediately in 58% of cases, one to 24 hours later in 20%, and more than 24 hours later in 9%. A delay is not reassurance. The American Society for Dermatologic Surgery task force calls this an ophthalmologic emergency, puts the most cited window for restoring blood flow at 90 minutes, and notes newer literature suggesting the window may be as little as 10 to 15 minutes.
In the United States that means calling 911 or going to an emergency department now. Reporting comes afterwards, and the channels are at where to report.
Nothing in this section is a way to assess yourself, and it is not written as one. These are the signs the regulator and the clinical literature describe as reasons to get in front of a clinician immediately, and all of them route to the same place.
Questions the record supports asking
- Which product is being used, and is it FDA-approved for the specific area being treated?
- Is that area on FDA’s list of sites it recommends against injecting — between the eyebrows, the nose, around the eyes, the forehead or the neck?
- What is the written plan if a vessel is occluded: who treats it, where, and how quickly?
- Is hyaluronidase on the premises during the appointment, and is it understood that this use of it is off-label and has not been evaluated by FDA?
- Which eye specialist or emergency service has been identified in advance, and how is it reached out of hours?
- Which symptoms should send someone to an emergency department rather than back to the treating clinic?
- If the product is not hyaluronic acid, what is the plan given that no enzyme removes it?
- What does the consent form say, in its own words, about vision loss and stroke?
Alternatives, including doing nothing
Doing nothing removes this risk completely. That is the only zero on this page, and it is worth stating because nothing else here produces one.
Changing the material does not change the mechanism, because an occlusion comes from placing a gel inside a vessel. What the material changes is the aftermath: only hyaluronic acid has an enzyme that degrades it, and the products sold on lasting longer are exactly the ones with no reversal agent at all.
Changing the site moves the odds and the stakes in different directions, and it does not remove the risk: FDA’s position, stated to its 2021 panel, is that nearly every anatomical location on the face carries a risk for blindness. Treatments that do not involve injecting a gel into facial tissue carry their own separate risks, covered in their own entries in the register, and not this one. Whether any of them addresses what a particular person wants addressed is what a consultation with a licensed clinician is for.
Sources
- US Food and Drug Administration, Dermal Fillers (Soft Tissue Fillers), content current as of 6 July 2023.
- US Food and Drug Administration, Executive Summary: General Issues Panel Meeting on Dermal Fillers, General and Plastic Surgery Devices Advisory Committee, 13 August 2025.
- US Food and Drug Administration, Executive Summary: General Issues Panel Meeting on Dermal Fillers, panel of 30 March 2021.
- US Food and Drug Administration, Center for Devices and Radiological Health, Clinical Overview of Dermal Fillers, advisory panel presentation, for the labelling text requested after the May 2015 safety communication.
- HYLENEX recombinant (hyaluronidase human injection) prescribing information, revised November 2024, via DailyMed, and Amphadase (hyaluronidase injection) prescribing information: both carry the same three indications, and the word filler appears in neither.
- Dermatologic Surgery 2015;41(10):1097–1117, Avoiding and Treating Blindness From Fillers: A Review of the World Literature, the first review in the lineage counted from 1906.
- Aesthetic Surgery Journal 2024;44(10):1091–1104, Update on Blindness From Filler: Review of Prognostic Factors, Management Approaches, and a Century of Published Cases.
- Aesthetic Surgery Journal 2019;39(6):662–674, Update on Avoiding and Treating Blindness From Fillers: A Recent Review of the World Literature.
- Plastic and Reconstructive Surgery — Global Open 2019;7(4):e2173, Soft-tissue Filler-associated Blindness: A Systematic Review of Case Reports and Case Series, with the comment at A Methodologic Concern Beyond Duplicated Cases.
- JAMA Dermatology 2021;157(2):174–180, Rates of Vascular Occlusion Associated With Using Needles vs Cannulas for Filler Injection.
- American Society for Dermatologic Surgery multidisciplinary task force, Preventing and Treating Adverse Events of Injectable Fillers: Evidence-Based Recommendations, Dermatologic Surgery 2021;47(2):214–226.
- Aesthetic Surgery Journal 2026;46(5):563–568, Consensus Guidelines for the Management of Tissue Filler-Induced Vision Loss in the United Kingdom.
Reviewed: 8 August 2026 · Evidence current to: 8 August 2026