What is actually in a filler syringe, and how the body takes it apart
FDA’s own page on filler materials puts the effect of hyaluronic acid at approximately 6 to 12 months. Magnetic resonance imaging keeps disagreeing: a 2024 review of 33 patients found gel in all of them, none fully gone at two years and one still visible after 15. And of the four materials FDA has approved to fill a face, only one has an enzyme that takes it apart.
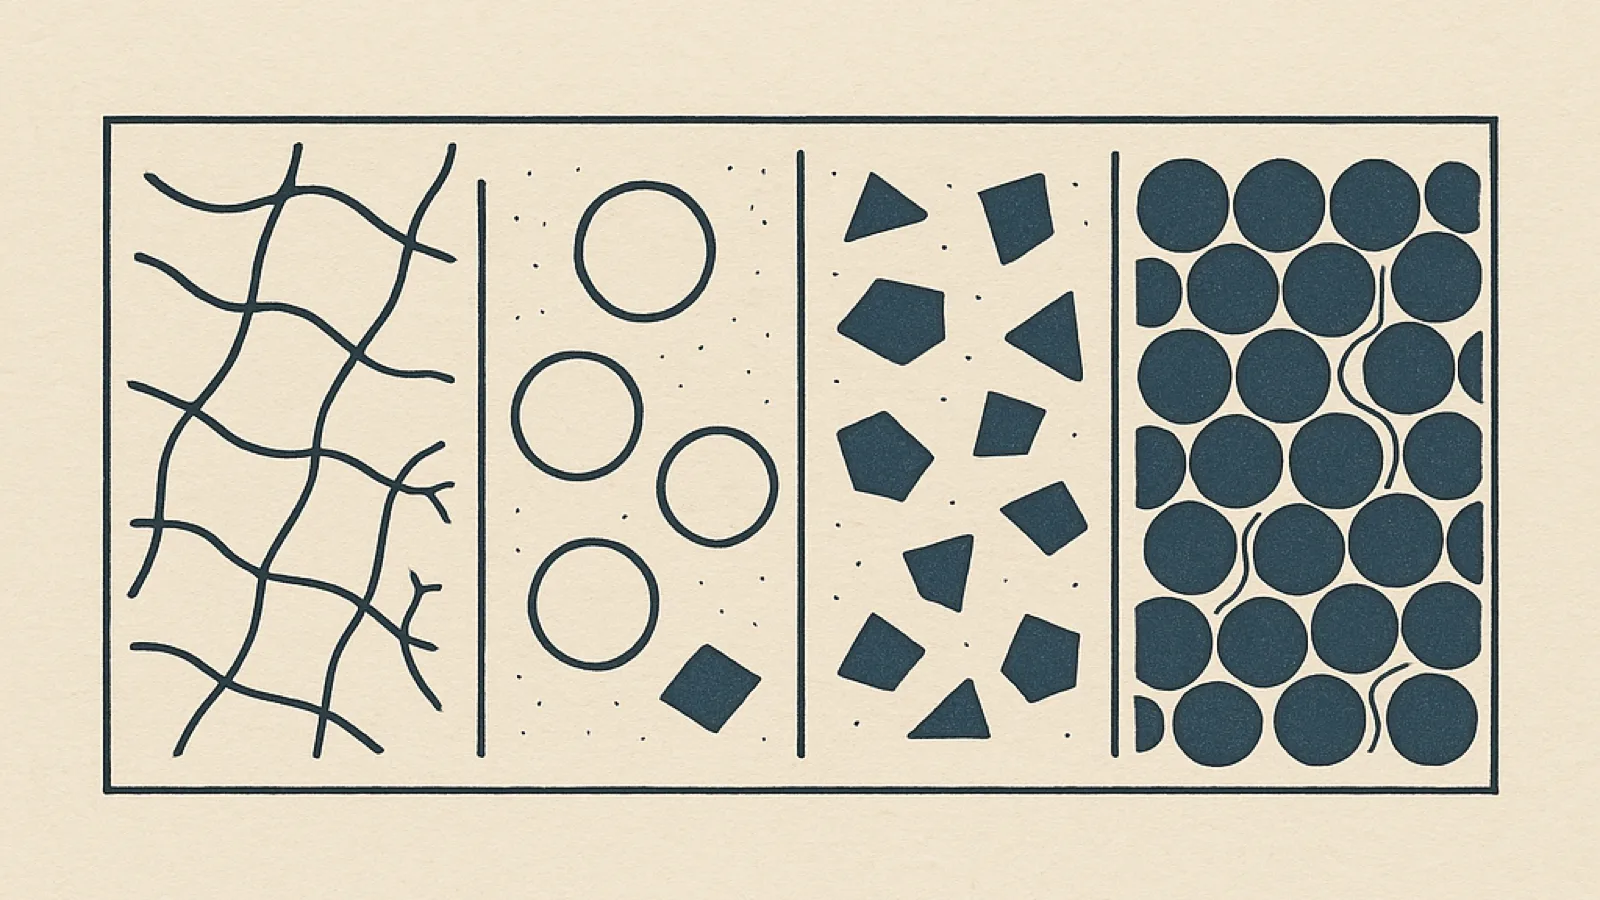
What it actually is
Four materials share one word. FDA’s page on what approved dermal fillers are made of names hyaluronic acid, calcium hydroxylapatite and poly-L-lactic acid as absorbable, and polymethylmethacrylate beads as the one exception: “The FDA has approved only one product made from a material that remains in the body and is not absorbed.” A price quoted for “filler” names a shelf, not a substance.
Hyaluronic acid is a sugar chain the body already makes and already dismantles. A 1997 review in the Journal of Internal Medicine put its half-life in tissues at less than one day to several days. Everything that makes a filler a filler is the chemistry added to slow that down.
That chemistry is crosslinking, and in almost every marketed gel the crosslinker is BDDE, 1,4-butanediol diglycidyl ether. Its reactive ends bond to the sugar chains and tie them into the mesh in Figure 2. A 2013 review in Dermatologic Surgery reports that once the reaction completes those groups are neutralised and only trace unreacted BDDE remains, below two parts per million. A 2008 paper in the Journal of Cosmetic and Laser Therapy lists what then separates one product from another: crosslink degree, gel hardness, concentration, hydration. Firmness is a manufacturing setting, not a brand personality.
Degradation follows from the same picture, and it is why the calendar never holds. The body’s own enzyme cuts the sugar chain wherever it can reach it, and free radicals attack it chemically. The mesh does not stop either process: FDA’s account of why the material is crosslinked at all is that it is chemically modified “to make it last longer in the body”, which is a claim about slowing degradation rather than preventing it. The gel is eroded unevenly rather than consumed on a schedule, at a rate set by how tightly it was tied and by the tissue around it.
The other three work differently. Calcium hydroxylapatite is a mineral found in teeth and bone, supplied as particles in a gel carrier; FDA notes it is visible in x-rays, and puts its effect at approximately 18 months. Poly-L-lactic acid is a polymer also used in absorbable stitches and bone screws, given in a series of injections over months, with effects that grow “increasingly apparent over time” and may last up to two years. Polymethylmethacrylate is beads in a bovine collagen gel; the collagen is absorbed and the beads are not.
“Biostimulator” is a marketing category, not a regulatory one: it describes products sold on the claim that the result comes from new collagen around the material rather than from the volume placed. FDA’s description carries one consequence of that — the effect becomes “increasingly apparent over time” — and the poly-L-lactic acid product’s own patient labelling carries the other: “It may seem that your treatment worked immediately because of swelling caused by injection and the water used to dilute SCULPTRA Aesthetic. This usually resolves in several hours to a few days and may cause the original wrinkle to reappear.” The volume in the mirror on the day is not, on the label’s own account, the material doing its job.
What it is approved for
From the label
FDA has approved dermal fillers for use in adults 22 years of age or older: absorbable ones for moderate to severe facial wrinkles and folds, for augmentation of the lips, cheeks, chin and back of the hand, and for facial fat loss in people with HIV; non-absorbable ones “for only nasolabial folds and cheek acne scars”.
Under the heading Unapproved Uses, FDA lists injection to increase breast size, buttock size or fullness of the feet, implantation into bone, tendon, ligament or muscle, and injection of “the glabella (area between eyebrows), nose, periorbital area (around the eyes), forehead, or neck”, then states plainly: “These uses for dermal fillers are not approved by the FDA.” Several of those placements are heavily marketed.
FDA also sets out who has not been studied: “The safety of these products is unknown when used during pregnancy, while breast feeding, and in patients under 22 years of age,” and unknown again “in patients who are prone to excessive scarring (keloids or hypertrophic scars)”.
Source: US Food and Drug Administration, Dermal Fillers (Soft Tissue Fillers), content current as of 6 July 2023, and FDA-Approved Dermal Fillers, content current as of 9 November 2020.
FDA PMA database
2003–2026
rung: label
Each product is approved individually through premarket approval, and the dates say more than any brand page. On the certainty ladder this is the top rung, because it quotes the record. Restylane was approved on 12 December 2003, Juvederm on 2 June 2006 and Radiesse on 22 December 2006 — the last gaining hand augmentation in 2015, jawline contour in 2021 and décolleté wrinkles in March 2026, an approval that grew site by site over twenty years. Both collagen stimulators arrived through medicine rather than cosmetics: Sculptra was approved on 3 August 2004 for facial fat loss in people with HIV, its cosmetic indication following on 28 July 2009, and the polymethylmethacrylate product as ArteFill in October 2006 for nasolabial folds, then as Bellafill in December 2014 for those folds plus cheek acne scars in patients over 21. Anything outside those wordings is off-label, which is lawful and common and is not the same as studied.
What the evidence establishes
Device PMA trials
rung: consistent trials
Randomised device trials consistently find that these products improve a scored wrinkle or fold severity rating against an untreated control or a comparator gel over the months after placement. That is the evidence behind every approval above, and it is real. It is also narrow: the outcome is a severity score read by an evaluator, the comparison is usually against another filler rather than against nothing, and the follow-up is counted in months.
For poly-L-lactic acid the shape of the field is visible in the numbers. A systematic review in Polymers in 2024 screened 1,467 citations to find 11 randomised controlled trials it could use. Four showed increased dermal thickness and improvement in lipoatrophy severity and aesthetic scores sustained for at least 25 months; two found it outperformed injectable human collagen. The review judged five of the eleven to be at high risk of bias, and its verdict on the field is blunter than any single result in it: the evidence is “of low quality”, so the reported effectiveness, safety and long-lasting effects “should be further investigated”.
One line of evidence comes from tissue rather than from imaging. A retrospective review in Dermatologic Surgery in 2022 examined frozen sections from 36 patients in whom hyaluronic acid filler turned up incidentally during Mohs micrographic surgery. It was found up to 10.75 years after implantation in one patient, and at three years or more in 36.8% (7 of 19) of those who could remember being injected. That series also found no granulomatous or giant cell response at any time period — persistence and foreign-body reaction are different questions, and the second came back negative.
Where the evidence runs out
MRI persistence series
2022–2026
rung: limited
The evidence on how long the gel stays put is limited to a small number of imaging studies, and they point the same way. In a review published in Plastic and Reconstructive Surgery – Global Open in July 2024, 33 patients who had received mid-face filler were imaged by MRI and read by two blinded radiologists. Filler was found in all 33, none of it fully dissipated at two years; twelve had not been injected for over five years, and the longest interval was 15. Set that against FDA’s figure of approximately 6 to 12 months. Three things stop it being settled: 33 people scanned at a single imaging centre in Australia, 24 of them recruited through referral networks and nine added retrospectively because they were concerned about periorbital or malar swelling, so this is not a random sample of treated faces; the authors’ own record that injection techniques, locations and volumes were often poorly recalled or poorly documented; and their own call for larger cohorts. It is a strong signal that the quoted duration is wrong, not a measurement of how wrong.
Where the gel sits appears to matter more than when it was placed. A single-patient case report in the same journal in 2022 followed material injected into the lateral face, the deep midface compartments and the chin: MRI showed almost complete degradation in the chin by 19 months, and persistence in the lateral face and deep midface at 27 months. One patient — and the proposed explanation, that a more mobile region clears gel faster, has not been tested in a series.
A third study checked something nobody had. A cross-sectional three-dimensional MRI study of 14 patients, in the same journal in 2026, compared the volume recorded as injected with the volume the scanner could measure. Measured exceeded injected at a ratio of about 1:2.8 — totals of 0.7 to 38 cm³ against 0.55 to 11 cm³ recorded. The authors call it the first comparison of its kind and offer hydration of the gel as the explanation. It rests on fourteen people and on those records being accurate. Treat the ratio as a flag, not a constant.
FDA, dermal fillers
6 July 2023
rung: not evaluated
Then the arithmetic, which is only arithmetic. If gel remains detectable at two years in every patient imaged, a course repeated every twelve months puts new material into a compartment the previous placement has not left. Over ten years that is ten placements and some unknown fraction of nine of them still there. Nobody has measured what the total becomes, and FDA says as much: “The safety of these products used repeatedly over a long period of time has not been evaluated in a controlled, clinical study.” The same page adds that their safe use alongside neuromodulators or other treatments has not been evaluated either — which covers filler given in the same appointment as botulinum toxin.
One limit runs the other way. An MRI signal is evidence that material is present, not that it is doing anything a person would notice in a mirror; a gel that has dispersed through a fat compartment still lights up a scan. The imaging work establishes persistence, and persistence is not duration of effect. The study that would settle that has not been done.
What it costs, and how it is priced
Filler is sold by the syringe, and the syringe is a volume of gel. Two quotes for “one syringe” can describe different volumes of differently crosslinked material, and neither number describes an amount of correction. There is no unit of result in this market, only a unit of product. The collagen stimulators are sold by the vial across a course, and FDA’s description of poly-L-lactic acid — given “in a series of injections over a period of several months” — makes the session count part of the product’s design rather than an upsell.
The repeat interval is itself a pricing assumption, and a schedule built on annual replacement is a commercial arrangement first. The imaging evidence above sits awkwardly beside it, and that is the tension to carry into any duration figure in this category, whoever is quoting it.
Risks and side effects
Common
FDA lists bruising, redness, swelling, pain, tenderness, itching and rash — and, observed only when filler is injected into the back of the hand, difficulty in performing activities. Most appear shortly after injection and many resolve within days to weeks. FDA also notes side effects can appear weeks, months or years later, which is unusual language for a common-risk list.
Less common
Inflammation near the site after a viral or bacterial illness, a vaccination or a dental procedure. Nodules or granulomas that may need injections, oral antibiotics or surgical removal. Infection, open or draining wounds, a sore at the site, allergic reaction, necrosis. FDA separately advises allergy testing before fillers made with animal-derived materials — which is why the bovine collagen carrier matters.
FDA also lists conditions it says a person should raise before the procedure: inflamed or infected skin, where it says injection “should be delayed”; a bleeding disorder; severe allergies or a history of anaphylaxis; allergy to collagen, eggs, animal products, local anaesthetics such as lidocaine, or bacteria, since different products contain each of those; and, for hand augmentation, joint, tendon or blood vessel disease affecting the hand.
Rare but serious
Among rare risks reported to FDA: anaphylactic shock; migration from the injection site; leakage or rupture through the skin; permanent hard nodules; injury to the blood supply from unintended injection into a blood vessel, resulting in tissue death, vision abnormalities including blindness, or stroke; and death. That last group changes what the treatment is, and it has its own article here: what matters in the first ten minutes is not the chemistry on this page.
Migration case series
2015–2021
rung: uncertain
Migration deserves defusing carefully, because the version circulating online and the version in the literature are not the same thing. It is not clear how often it happens. FDA places it among rare reported risks, and the published record is case reports and small series: a 2015 paper in Ophthalmic Plastic and Reconstructive Surgery reporting three cases, and a 2021 multicentre series in Aesthetic Surgery Journal describing seven patients in whom facial filler was later found in the orbit, which its authors call a newly reported complication. Against that, the 2022 MRI case report above looked for movement and found none at 27 months. This publication could not trace the percentages repeated on social media to any study that measured a rate, so it prints none.
Can it be undone
“You should be aware that it may be difficult or impossible to remove the filler material, especially ‘permanent’ fillers, or fillers that are not made of materials such as hyaluronic acid (HA).”
US Food and Drug Administration, Dermal Fillers (Soft Tissue Fillers), content current as of 6 July 2023.Hylenex label, rev. 11/2024
JCM review 2025
rung: limited
Hyaluronidase works on hyaluronic acid for a chemical reason: it cleaves the same bonds that hold the sugar chain together. What it is approved for is another matter. The prescribing information for the recombinant human product — initial US approval 2005, revised November 2024 — gives its indications as an adjuvant in subcutaneous fluid administration, to increase the dispersion and absorption of other injected drugs, and in subcutaneous urography. The words “filler” and “dermal filler” appear nowhere in it. Dissolving filler is an off-label use of an approved drug. The same label gives hypersensitivity as a contraindication and records that “allergic and anaphylactic-like reactions have been reported, rarely”, so the enzyme is not a neutral undo button; it is a second injected drug with a risk profile of its own.
It is also unstandardised. A 2025 review in the Journal of Clinical Medicine, covering cases reported from 2020 to 2025, records great variability in dosage and protocol and calls for standardisation. The controlled evidence is thin: a blinded randomised study in Dermatologic Surgery in 2017 injected seven marketed gels into the backs of 15 participants and found two enzyme concentrations both reduced the filler, with the higher no better than the lower. Fifteen participants is the whole of it.
None of this reaches the other three materials, because none is a hyaluronan and none carries the bond the enzyme cuts. Sodium thiosulfate has been proposed for calcium hydroxylapatite and tested at the bench, and the bench results do not agree with each other. A cadaveric and in-vitro study in Aesthetic Surgery Journal in 2021 filled human facial artery segments with the product, submerged them for 24 hours in four thiosulfate solutions, and still detected the material at every concentration, including in combination with hyaluronidase. A 2020 preclinical study in Clinical, Cosmetic and Investigational Dermatology — written by the research arm of the company that markets that product, which is worth knowing and cuts both ways — records that earlier small pilot studies had suggested the agent reduced filler volume and nodules, then reports no indication of degradation in vitro or in a pig model, attributes the reduction its imaging did show to dispersion rather than dissolution, and reports necrosis and haemorrhage after treatment. There is no approved reversal agent for any of the three materials, and polymethylmethacrylate is classed by FDA as non-absorbable — a design property, not a defect.
So “reversible” is a property of a chemistry, not of “filler”. The word is accurate for one of the four materials, off-label in the very use that makes it accurate, and false for the rest.
When to seek urgent care
Emergency signs, in FDA’s words
FDA instructs people to “seek immediate medical attention if you experience unusual pain, vision changes, a white, gray, or blue appearance of skin near the injection site, or any signs of a stroke (including sudden difficulty speaking, numbness or weakness in your face, arms, or legs, difficulty walking, visual changes, face drooping, severe headache, dizziness, or confusion) during or shortly after the procedure.”
That is an emergency department instruction, not a message to leave with a clinic. What the literature describes clinicians watching for is set out at filler in a blood vessel. Problems with an FDA-regulated product can be reported afterwards at where to report; reporting is not a substitute for care.
Questions the record supports asking
- Which of the four materials is in the syringe, is it absorbable or non-absorbable, and which FDA premarket approval covers it for the area being treated?
- If it is hyaluronic acid, what is the plan if it has to come out, and is that use on the enzyme’s approved label?
- If it is one of the other three, what is the plan if the result is not wanted, given that no enzyme removes them?
- Where does the quoted duration come from, and does it describe the material or the effect?
- Has this area been injected before, and is that material likely to still be there?
- What record is kept of the product name, lot number and volume placed, and can a copy be provided?
Alternatives, including doing nothing
Doing nothing is a real option, and the record makes it easy to state. Every approved indication above concerns the appearance of wrinkles, folds and contour. No filler treats a disease, and nothing in the regulatory record establishes a health consequence of leaving a nasolabial fold alone. The exception is the indication these products arrived under — facial fat loss in people with HIV — a clinical situation rather than a menu item.
Among the alternatives that are not nothing, the distinction that matters is chemical rather than commercial. Botulinum toxin acts on muscle rather than volume, is a drug rather than a device, and has its own row in the register. Within filler, absorbable against non-absorbable is the choice that cannot be revisited: a gel that degrades leaves the option of changing your mind, at the cost of repeating the procedure; one that does not removes that option in exchange for not repeating it.
Whether any of it suits a particular person depends on their medical history, the medicines they take and what the tissue in that area is doing. Establishing that is what a consultation with a licensed clinician is for.
Sources
- US Food and Drug Administration. Dermal Fillers (Soft Tissue Fillers). Content current as of 6 July 2023.
- US Food and Drug Administration. FDA-Approved Dermal Fillers. Content current as of 9 November 2020. The four materials and their approximate durations.
- US Food and Drug Administration, Premarket Approval database, retrieved 8 August 2026: P020023, Restylane; P050047, Juvederm; P050052, Radiesse (original approval 22 December 2006; hand augmentation S049, 4 June 2015; jawline contour S129, 1 September 2021; décolleté wrinkles S162, 31 March 2026); P030050, Sculptra; P020012, ArteFill / Bellafill.
- US Food and Drug Administration. SCULPTRA Aesthetic, labeling for physicians and patients (PMA P030050/S002). The patient section on why an immediate result is not the material working.
- Journal of Internal Medicine, 1997;242(1):27–33. Hyaluronan: its nature, distribution, functions and turnover.
- Dermatologic Surgery, 2013;39(12):1758–1766. A review of the metabolism of 1,4-butanediol diglycidyl ether-crosslinked hyaluronic acid dermal fillers.
- Journal of Cosmetic and Laser Therapy, 2008;10(1):35–42. The science of hyaluronic acid dermal fillers.
- Plastic and Reconstructive Surgery – Global Open, 2024;12(7):e5934. Hyaluronic Acid Filler Longevity in the Mid-face: A Review of 33 Magnetic Resonance Imaging Studies.
- Plastic and Reconstructive Surgery – Global Open, 2022;10(4):e4252. Long-term MRI Follow-up of Hyaluronic Acid Dermal Filler. A single-patient case report.
- Plastic and Reconstructive Surgery – Global Open, 2026;14(7):e7894. Longevity and Volume Expansion of Hyaluronic Acid Dermal Fillers: A Cross-sectional 3-dimensional Magnetic Resonance Imaging Study. Fourteen patients.
- Dermatologic Surgery, 2022;48(4):401–405. Hyaluronic Acid Filler Incidentally Found During Mohs Micrographic Surgery: Observations in 36 Patients.
- Polymers, 2024;16(18):2564. Efficacy and Safety of Poly-l-Lactic Acid in Facial Aesthetics: A Systematic Review.
- DailyMed, US National Library of Medicine. HYLENEX recombinant (hyaluronidase human injection) prescribing information. Initial US approval 2005; revised November 2024.
- Journal of Clinical Medicine, 2025;15(1):279. Hyaluronidase Use in Aesthetic Medicine: Formulations, Safety, and Clinical Practice.
- Dermatologic Surgery, 2017;43(6):841–847. The Kinetics of Reversible Hyaluronic Acid Filler Injection Treated With Hyaluronidase. Fifteen participants.
- Aesthetic Surgery Journal, 2021;41(5):NP226–NP236. Intraarterial Degradation of Calcium Hydroxylapatite Using Sodium Thiosulfate — An In Vitro and Cadaveric Study.
- Clinical, Cosmetic and Investigational Dermatology, 2020;13:1059–1073. Can Sodium Thiosulfate Act as a Reversal Agent for Calcium Hydroxylapatite Filler? Results of a Preclinical Study. Authors from the R&D and medical affairs arms of the product’s manufacturer.
- Ophthalmic Plastic and Reconstructive Surgery, 2015;31(4):257–262. Filler Migration: A Number of Mechanisms to Consider. Three cases.
- Aesthetic Surgery Journal, 2021;41(6):NP559–NP566. Filler Migration to the Orbit. Seven patients.
Reviewed: 8 August 2026 · Evidence current to: 8 August 2026