Botulinum toxin: the best-evidenced treatment in aesthetics, and the four claims that outrun the evidence
This is the strongest case in non-surgical aesthetics, and the honest place to start: the approved cosmetic uses rest on randomised, placebo-controlled trials whose numbers are printed in the label. That same label carries a boxed warning for spread beyond the injection site, and states that this product’s Units cannot be converted into any other product’s Units — which breaks the per-unit price comparison between one product and another.
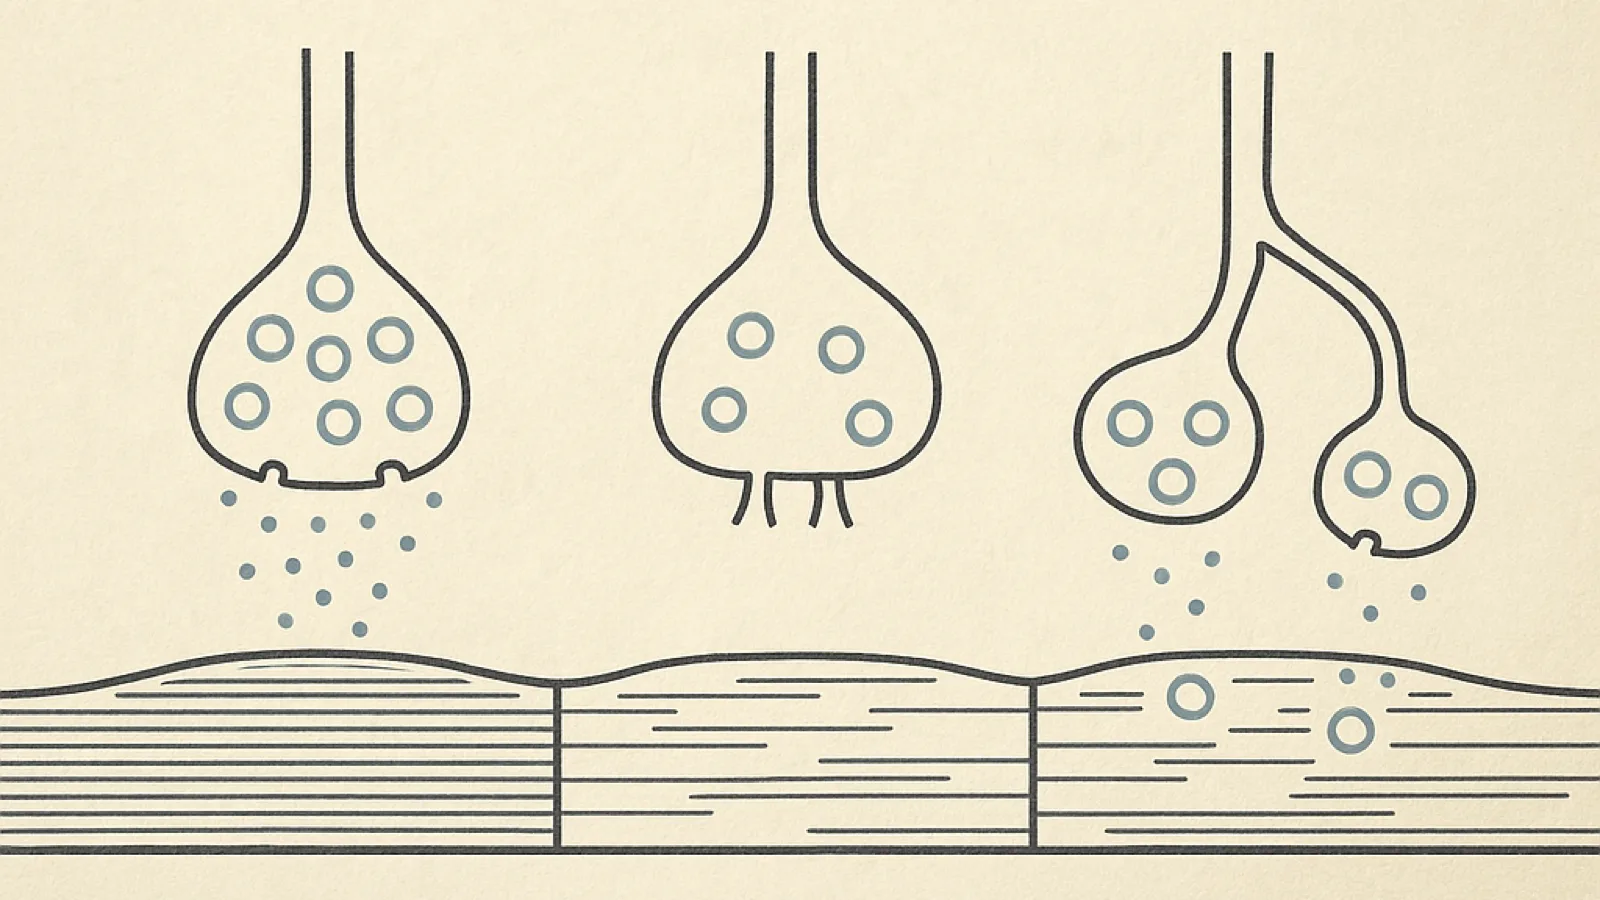
What it actually is
BOTOX Cosmetic prescribing information, §12.1, revised 10/2024. What the rung marks mean.
Botulinum toxin stops a nerve ending from telling a muscle to contract. The label describes it directly: the toxin binds to acceptor sites on motor nerve terminals, enters them, and cuts the protein the nerve needs in order to release its signal — SNAP-25. Without it, the packets of acetylcholine inside the nerve ending cannot dock and empty into the neuromuscular junction. The label’s term is partial chemical denervation: the muscle is disconnected, and only partly.
The part almost nobody explains is why it comes back, and the label explains it in a sentence: there is evidence that reinnervation of the muscle may occur, thus slowly reversing the denervation. The nerve does not stay cut; it sprouts new endings and function returns. A newer product’s label puts it more plainly — recovery happens gradually as the junction recovers from SNAP-25 cleavage and as new nerve endings are formed.
So duration is a biology question — how fast a particular nerve regrows its connections, which varies between people and muscles. A result that lasts longer in one person is not evidence of a better product.
From the label
Indication. BOTOX Cosmetic (onabotulinumtoxinA) is indicated in adult patients for the temporary improvement in the appearance of moderate to severe glabellar lines, lateral canthal lines, forehead lines and platysma bands, each tied to a named muscle; initial US approval 1989, platysma bands newest. Approved populations differ: abobotulinumtoxinA’s cosmetic indication is written for adults under 65.
Boxed warning. Postmarketing reports indicate the effects of this and all botulinum toxin products may spread from the area of injection — weakness, generalised muscle weakness, double vision, drooping eyelids, difficulty swallowing, voice change, slurred speech, loss of bladder control, breathing difficulty — hours to weeks afterwards. Swallowing and breathing difficulties can be life threatening and there have been reports of death. The warning records that spread has been reported both in unapproved uses and in approved indications, at doses comparable to or lower than those used to treat cervical dystonia and spasticity.
And the sentence that is not in it. A separate line in section 5.2, outside the boxed warning, says no definitive serious adverse event reports of distant spread have been reported for dermatologic use at the labelled dose — then enumerates which doses it means: 20, 24, 40, 44, 64 and 100 Units. The platysma band doses of 26, 31 and 36 Units, approved in October 2024, are not on that list. It is a statement about six specific doses, not a general assurance, and it is routinely quoted as though it were the latter.
Anything sold as a cosmetic “tox” treatment outside those four indications — masseter slimming, the lip flip, shoulders, calves, scalp — is an off-label use. That is lawful and ordinary, and it means the trials in the label do not describe what is being done.
What the evidence establishes
BOTOX Cosmetic prescribing information, §14.1 (Tables 8–10) and §14.4 (Table 15).
Two randomised, double-blind, placebo-controlled studies of identical design supported the glabellar line indication (405 treated, 132 placebo). At day 30 investigators rated the lines none or mild in 80% of treated participants against 3% on placebo; participants’ own ratings of moderate or better improvement ran 89% against 7%. Randomised trials separate this drug from placebo on the lines it is approved for, and they do it repeatedly. Nothing else in non-surgical aesthetics has a comparable record.
Consistent is not the same as large, and the newest indication shows it. The two trials behind the platysma band approval (408 treated, 426 placebo) used a stricter primary endpoint — minimal or mild severity and at least a two-grade improvement, agreed independently by investigator and participant — and met it in 32% and 31% of treated participants at day 14, against 2% and 0% on placebo. Same drug, same label, a responder rate under half the headline glabellar figure, because the bar was set higher and the target is harder. A percentage from one indication tells you nothing about another.
The label also prints the unflattering numbers. Of the 23 glabellar-line participants aged 65 or over who received the drug, the investigator responder rate at day 30 was 39% — 9 of 23 — against 83% among those under 65. The label calls that a lower treatment-associated response and notes the number of older participants was limited. Read the arithmetic and the caution is the honest part: 2 of the 9 older placebo recipients were rated responders too, leaving a difference of 17 percentage points whose 95% confidence interval runs from −17 to 51. In a group that small the true effect could be nothing or could be large. What the pivotal data establish about people over 65 is mainly that they were barely studied.
Where the evidence runs out
A day-30 rating-scale effect does not establish four things said about this treatment daily.
One: a Unit is a property of the manufacturer’s own assay
BOTOX Cosmetic prescribing information, §5.1 and §11; matching statements in the DYSPORT, XEOMIN and DAXXIFY labelling.
Ask what a Unit is and the label answers with a laboratory procedure, not a quantity of drug: one Unit corresponds to the calculated median intraperitoneal lethal dose in mice, and the assay actually used to release each batch is, in the label’s words, specific to that manufacturer’s own products. The consequence appears in every approved product’s warnings — Units of one product cannot be compared to nor converted into Units of any other botulinum toxin product assessed with any other specific assay method.
The gap is visible in the labels: for glabellar lines, abobotulinumtoxinA’s approved total is 50 Units against onabotulinumtoxinA’s 20, two and a half times the number, while incobotulinumtoxinA’s is 20, exactly the same number. A 2016 review in Toxins collected published conversion ratios ranging from 1:1 to 1:11 and concluded that a ratio of 3:1 or lower between abobotulinumtoxinA and onabotulinumtoxinA could be appropriate — but that literature comes from spasticity and dystonia, not cosmetic use, and no conversion factor is approved by anyone. A 2024 review in the same journal, by employees of the company that makes BOTOX, records that the regulator has required a non-interchangeability statement in every label since 2000.
Two clinics quoting different amounts per unit may be charging the same money for the same effect, or wildly different money, and the arithmetic that would separate them does not exist. Within one product the comparison is real; across products it is not one at all.
Two: nobody has established which product lasts longer
BOTOX Cosmetic prescribing information, §2.4 and §14.1, Tables 8–9.
The label puts the duration of effect for glabellar lines at approximately three to four months, then shows what that average conceals. The investigator responder rate falls from 80% at day 30 to 70% at day 60, 48% at day 90 and 25% at day 120; participants’ own ratings fall more slowly — 89%, 82%, 63%, 39%. Duration is a curve, and the two people rating the same face disagree about where it ends.
DAXXIFY prescribing information, §14, Studies GL-1 and GL-2; sponsor’s pooled analysis, J Am Acad Dermatol 2020; phase 2 comparison, Dermatol Surg 2017.
The longest duration claim attaches to daxibotulinumtoxinA. Its label prints no duration figure at all. What it prints is a week-4 treatment success rate of 74% against 0% on placebo across two trials (406 treated, 203 placebo), and a graph running to 36 weeks in which participants were discontinued once both ratings had returned to baseline and thereafter counted as non-responders. The six-month figure comes from the sponsor’s own pooled publication of those same two trials, which reports that none-or-mild severity was maintained for a median of 24.0 weeks; several of its authors are employees of the manufacturer.
Head-to-head evidence does exist, and it is thinner than what is built on it. The relevant trial is a phase 2 study run by that same sponsor — 268 participants, published in Dermatologic Surgery in 2017 — reporting a median duration of response of 24 weeks for 40 Units of daxibotulinumtoxinA against 19 weeks for 20 Units of onabotulinumtoxinA. Read what was compared: 40 Units of one product against 20 Units of another, in a currency the labels themselves say does not convert. A trial like that can show that one dose of one product outlasted one dose of another. It cannot show which product lasts longer, because no dose at which the two are equivalent has ever been established. The claim sits on the contested rung.
Three: “preventative” treatment of a face with no lines is unsupported
Arch Facial Plast Surg 2006 (case report, n=2); systematic review in Muscles, 2025.
The idea that starting early prevents lines rests almost entirely on one paper: a 2006 comparison of identical twin sisters, one treated in the forehead and glabella two or three times a year for thirteen years, the other twice. Lines visible at rest were absent in the frequently treated twin. It is indexed as a case report — two people, unblinded, comparing more treatment against less in adults, not an unlined face against leaving it alone.
A 2025 systematic review in Muscles addressed exactly this question. It identified 1,327 records, screened 803 after deduplication, included nine studies, declined to pool them because their designs differed too much, and concluded that long-term outcomes are not yet fully established. None of the nine tests treating an unlined face to stop lines forming: they are trials in adults who already had moderate to severe lines, plus studies of intradermal injection for skin texture and of rosacea redness. It is not clear whether treating an unlined face changes anything, because that study has not been done.
Four: resistance is overstated at cosmetic doses
BOTOX Cosmetic prescribing information, §12.6; review in Arch Plast Surg, 2022.
Antibody-mediated resistance is real, documented mainly where doses are large and repeated — therapeutic uses, not cosmetic ones. The label reports that of 916 participants in three lateral canthal line trials, 14 (1.5%) developed binding antibodies and none developed neutralising antibodies. A 2022 review in Archives of Plastic Surgery makes the dose point: aesthetic indications use lower doses, and a pivotal aesthetic study reported no treatment failure attributable to antibodies.
Two caveats stop that being reassurance. The label says the critical factors for neutralising antibody formation have not been well characterised, and that more frequent injections or higher doses may raise the incidence. And someone who stops responding has not been shown to have antibodies: the same review describes the detection tools disagreeing, the mouse protection assay offering full specificity but sensitivity under 50%.
The supply chain, and what happens when it fails
CDC investigation page, updated 17 December 2024; MMWR 2024;73(27):609–611; MMWR 2025;74(38):593–596.
When the chain that delivers this prescription biologic breaks, the failure does not look like a poor result. It looks like botulism.
The 2024 investigation by the Centers for Disease Control and Prevention, state health departments and the Food and Drug Administration is closed, recording 17 cases in nine states, 13 hospitalisations and no deaths. That number moved: an early update counted 22 people in eleven states; a later one counted 15, after seven were excluded as having received approved product properly administered; the final count was 17. A running case count describes an investigation, not a population.
Two Morbidity and Mortality Weekly Report notes carry the clinical detail. The first describes seven women who became ill in early 2024 after injections in non-medical settings — six in a residence, one in a cosmetic spa; four were hospitalised, two went to intensive care, and four had been injected by a relative not licensed to do it with product the regulator determined was counterfeit. The second, from November 2025, describes three women who bought botulinum toxin online — a retailer in Korea, vendors in China reached through a messaging app and a social platform — and injected themselves. All three were hospitalised, one needed mechanical ventilation, all received antitoxin, and all still had residual signs at discharge.
The Food and Drug Administration’s April 2024 alert set out how counterfeit cartons differed: a specific lot number, the active ingredient printed under a generic chemical description rather than the approved nonproprietary name, a vial strength the manufacturer does not make, and text not in English. Federal law, FDA notes, requires providers who dispense or administer prescription drugs to buy them only from authorised sources. The public guidance CDC attached to the closed investigation was narrow and worth quoting for its plainness: only get botulinum toxin injections if the product came from an authorised supplier and the provider is licensed and trained to give the injection, and if in doubt, don’t get the injection. Counterfeit product and harmful reactions both have official reporting routes, on where to report. The same supply question arises in a harder form for materials that have no US approval at all, and so no authorised source to buy from: mesotherapy, PRP, exosomes and polynucleotides.
What it costs, and how it is priced
The American Society of Plastic Surgeons reports an average surgeon or physician fee of $435 for a neuromodulator injection in its 2023 statistics, against $528 for 2022. Read the column heading before the number. It is an average of surgeon and physician fees drawn from that society’s annual survey of its own members — not a survey of clinics, not a price, and the document does not say what else appears on a bill. A drop of nearly a fifth in a single year says more about who answered the survey than about what anyone charges.
Charging by the unit makes the amount used visible and the arithmetic checkable, within one product. Charging by area hides the unit count, so an underwhelming result cannot be traced to a small amount of product or a resistant muscle. Neither is dishonest; only one leaves a record.
Risks and side effects
Ruled out by the label
Two contraindications are absolute in the labelling: known hypersensitivity to any botulinum toxin preparation or to any component of the formulation, and infection at the proposed injection site. Beyond those, the label warns that people with neuromuscular disorders — myasthenia gravis, Lambert-Eaton syndrome, amyotrophic lateral sclerosis, peripheral motor neuropathies — may be at increased risk of clinically significant effects, and that anyone taking aminoglycoside antibiotics, other agents that interfere with neuromuscular transmission, or muscle relaxants should be observed closely because the effect may be potentiated. It also advises caution in people with pre-existing cardiovascular disease, and in anyone with compromised respiratory function or existing difficulty swallowing.
On pregnancy the label is blunt about the gap rather than reassuring: there are no studies and no adequate postmarketing data on developmental risk in pregnant women, and in animals, dosing during pregnancy reduced fetal body weight and skeletal ossification at doses the label describes as clinically relevant. There are no data on its presence in human milk.
Common
In the placebo-controlled glabellar line studies, the reactions reported by at least 1% of treated participants and more often than on placebo were eyelid drooping in 13 of 405 (3%), facial pain and muscular weakness in 6 each (1%), and facial paresis in 5 (1%). In the forehead line studies (665 treated, 315 placebo): headache in 9% against 5% on placebo, eyelid drooping in 2% against 0%, brow drooping and skin tightness in 2% each against 0%. In the lateral canthal line studies, eyelid swelling in 1% against 0%. Separately from any table, the label states that localised pain, infection, inflammation, tenderness, swelling, redness and bruising may accompany the injection itself, and that reactions, while often transient, may last several months or longer.
Those figures belong to one product’s trials. Setting them beside a number from another label is not a comparison — the trials differ in design, population, scale and rater, which is the same reason the Units do not convert. The label says as much in its own words: because trials are conducted under widely varying conditions, rates observed in one drug’s trials cannot be directly compared with rates in another’s. No ranking of products by side-effect rate can honestly be built out of these numbers.
Less common
The label carries warnings for dry eye after injection in or near the muscle that closes the eye, and for reduced blinking leading to corneal exposure and, at worst, ulceration.
Rare but serious
The boxed warning is the serious tier, and applies to every approved product. Spread of effect has been reported hours to weeks afterwards, producing swallowing and breathing difficulty the label calls potentially life threatening, with reports of death; dysphagia may persist for months and may require a feeding tube, and the label records postmarketing reports of respiratory failure. Serious hypersensitivity reactions including anaphylaxis have been reported, as have cardiovascular events including arrhythmia and myocardial infarction, some fatal. People with neuromuscular disorders such as myasthenia gravis are at increased risk.
None of that makes these events likely. It does make any description of this treatment as free of risk unsupportable from its own labelling.
Can it be undone
No. There is no reversal agent, and the label is unambiguous about the limits of the one drug that exists: antitoxin is available from the CDC in cases of poisoning, but it will not reverse effects already apparent by the time it is given. It binds toxin still in the blood and cannot retrieve what has bound to a nerve terminal. Recovery from an unwanted effect is the same process as the wearing-off of a wanted one — reinnervation, on its own timetable. That is the sharpest practical difference from hyaluronic acid filler, where an enzyme exists that can degrade the material.
When to seek urgent care
If this is happening now
The labelling instructs prescribers to advise patients to seek immediate medical care if swallowing, speech or respiratory difficulties occur, and lists the signs of spread beyond the injection site: weakness, generalised muscle weakness, double vision, drooping eyelids, difficulty swallowing, voice change, slurred speech, loss of bladder control and breathing difficulty. It records that these have been reported anywhere from hours to weeks after an injection.
In the United States that means calling 911 or going to an emergency department now, and saying that a botulinum toxin injection was given and when. In the three 2025 cases CDC wrote up, the clinical teams suspected botulism only once the patient volunteered that history. CDC tells clinicians who suspect botulism to contact their state or local health department immediately, because antitoxin is released through that route; the label states that antitoxin will not reverse effects already apparent by the time it is given. Reporting comes afterwards, and the channels are at where to report.
Questions the record supports asking
- Which product is this, by its nonproprietary name — onabotulinumtoxinA, abobotulinumtoxinA, incobotulinumtoxinA, prabotulinumtoxinA, daxibotulinumtoxinA? The brand name alone does not identify the potency assay.
- Is this an approved cosmetic indication for that product, or an off-label use? Only one has trials in the label.
- Is the injector licensed and trained for this, and is the setting licensed?
- If quoted a figure per unit, is it the same product as one quoted elsewhere — and am I charged by unit or by area?
- Which warning signs should send me to an emergency department, and for how long?
- Is anything else injected in the same session, and what is known about that combination?
Alternatives, including doing nothing
Doing nothing is a real option with a known outcome: expression lines deepen with age, sun exposure and movement, and nothing about that is dangerous. It is the only option here with no boxed warning attached.
Nothing else does what this does, so the alternatives are alternatives only in the loose sense of addressing a different part of an ageing face. Of them, daily sunscreen carries the strongest randomised evidence: a community trial reported in Annals of Internal Medicine randomised 903 Australian adults under 55 to daily or discretionary sunscreen, and found skin ageing — graded from skin microtopography by assessors blinded to allocation — 24% lower in the daily group after four and a half years (relative odds 0.76, 95% CI 0.59 to 0.98). That is photoageing, not muscle-driven lines, and it substitutes for nothing described above. Lasers, peels and filler likewise address surface texture or lost volume rather than movement. Because they act on different things they are often sold together — and that combination is the clearest gap in the record.
FDA, Dermal Fillers (Soft Tissue Fillers), content current as of 6 July 2023.
In its consumer guidance on dermal fillers, the Food and Drug Administration states that the safe use of those products in combination with neuromodulators — it names “Botox” in parentheses — or with other treatments has not been evaluated in a controlled, clinical study. The regulator is not saying the combination is unsafe. It is saying the study that would settle the question has not been done. The other gap is longer-range: the pivotal trials ran for months and their repeat-treatment extensions for a few cycles over a year, so what repeated dosing does to a face over decades has not been evaluated either.
None of this is a judgement about any individual face. Whether a treatment is appropriate turns on medical history, current medicines and what the muscles and skin in that area are actually doing — and these are prescription products, so under the labelling that assessment belongs to the licensed clinician who would prescribe and administer them.
Sources
- BOTOX Cosmetic (onabotulinumtoxinA) prescribing information, revised 10/2024, DailyMed.
- DYSPORT (abobotulinumtoxinA) prescribing information, DailyMed.
- XEOMIN (incobotulinumtoxinA) prescribing information, DailyMed.
- DAXXIFY (daxibotulinumtoxinA-lanm) prescribing information, DailyMed.
- FDA, Counterfeit Version of Botox Found in Multiple States, issued 16 April 2024, content current as of 2 May 2024.
- CDC, Harmful Reactions Linked to Counterfeit “Botox” or Mishandled Botulinum Toxin Injections, updated 17 December 2024, with earlier counts in its update history.
- “Illnesses After Administration of Presumed Counterfeit Botulinum Toxin in Nonmedical Settings,” MMWR 2024;73(27):609–611.
- “Severe Illnesses After Self-Injection of Botulinum Toxin Purchased Online,” MMWR 2025;74(38):593–596.
- FDA, Dermal Fillers (Soft Tissue Fillers), content current as of 6 July 2023.
- “Conversion Ratio between Botox, Dysport, and Xeomin in Clinical Practice,” Toxins 2016;8(3):65.
- “Update on Non-Interchangeability of Botulinum Neurotoxin Products,” Toxins 2024;16(6):266 — by employees of AbbVie/Allergan Aesthetics, which makes BOTOX.
- “Long-term effects of botulinum toxin type A (Botox) on facial lines: a comparison in identical twins,” Archives of Facial Plastic Surgery 2006;8(6):426–431 (case report).
- “Evaluating the Preventive Role of Botulinum Toxin in Facial Aging,” Muscles 2025;4(3):31.
- “Immunogenicity of botulinum toxin,” Archives of Plastic Surgery 2022;49(1):12–18.
- “DaxibotulinumtoxinA for Injection has a prolonged duration of response in the treatment of glabellar lines: pooled data from SAKURA 1 and SAKURA 2,” J Am Acad Dermatol 2020;82(4):838–845 — several authors are employees of the manufacturer.
- “Injectable DaxibotulinumtoxinA for the Treatment of Glabellar Lines: A Phase 2, Randomized, Dose-Ranging, Double-Blind, Multicenter Comparison With OnabotulinumtoxinA and Placebo,” Dermatologic Surgery 2017;43(11):1321–1331.
- “Sunscreen and prevention of skin aging: a randomized trial,” Annals of Internal Medicine 2013;158(11):781–790.
- American Society of Plastic Surgeons, 2023 average surgeon/physician fees.
Expands the botulinum toxin row of the register.
Reviewed: 8 August 2026 · Evidence current to: 8 August 2026